Why Small Assisted Living Neighborhoods Excel at Medication and ADL Management
Business Name: BeeHive Homes of Taylor Ranch
Address: 6004 Whiteman Dr NW, Albuquerque, NM 87120
Phone: (505) 302-1919
BeeHive Homes of Taylor Ranch
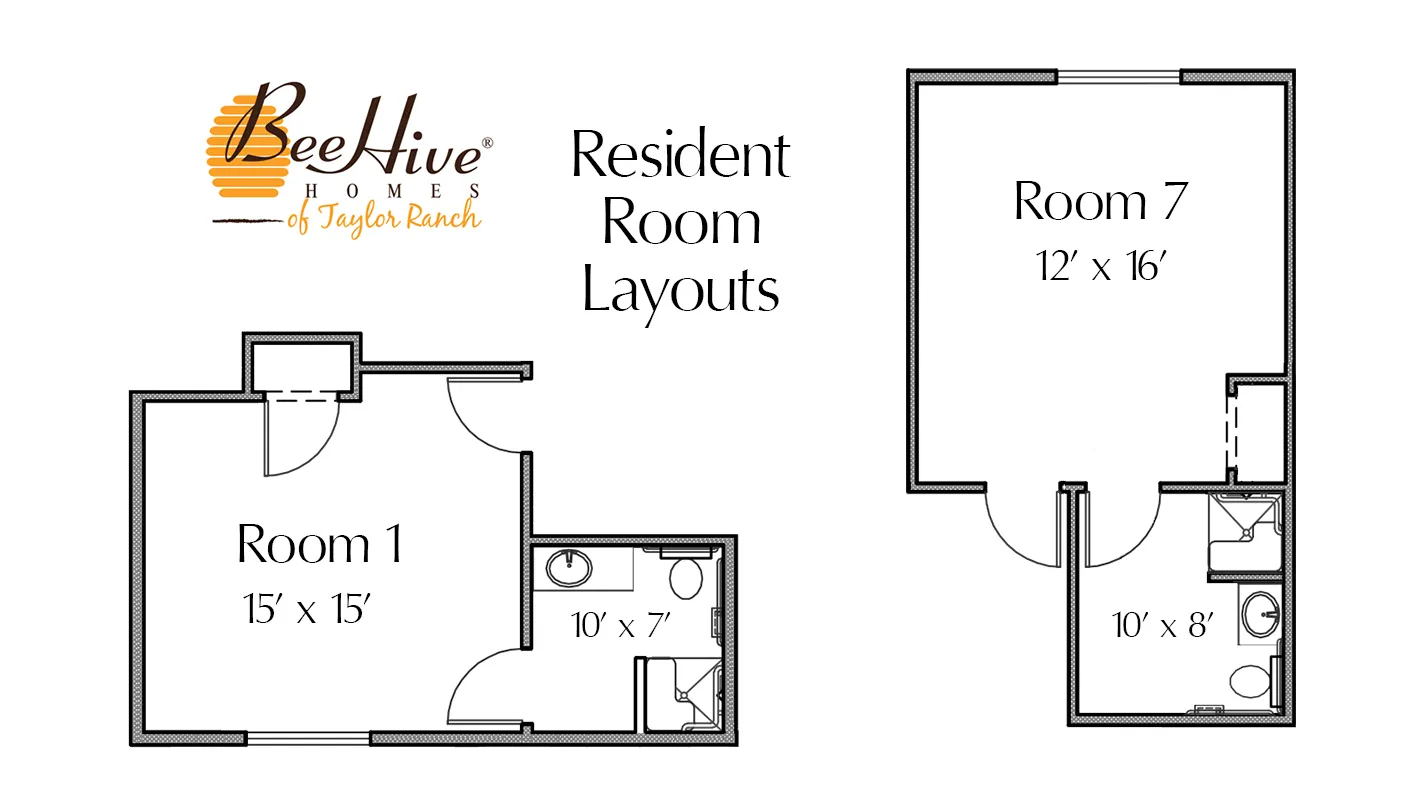
At BeeHive Homes of Taylor Ranch, New Mexico, we offer the finest assisted living experience available in a cozy, comfortable homelike setting. Each of our residents has their own spacious room with an ADA approved bathroom and shower. We prepare and serve delicious home-cooked meals three times a day every day. We maintain a small, friendly elderly care community. We provide regular activities that our residents find fun and contribute to their health and well-being. Our staff is attentive and caring and provides assistance with daily activities to our senior living residents in a loving and respectful manner. We would like to invite you to tour and experience our assisted living home and feel the difference.
6004 Whiteman Dr NW, Albuquerque, NM 87120
Business Hours
Families rarely tour an assisted living neighborhood due to the fact that life is going smoothly. Regularly, something has slipped: a medication mix‑up, a fall throughout a nighttime bathroom trip, a pot left on the range. By the time people start comparing senior care choices, they have currently seen how delicate everyday regimens can become.
Over the years I have watched both large and small neighborhoods deal with these issues. The difference in how they manage medications and activities of daily living, or ADLs, is rarely about better furnishings or a bigger lobby. It has to do with whether personnel actually understand each resident, notice tiny changes, and have adequate time and structure to act upon what they see.
Small assisted living neighborhoods are not perfect, and they are wrong for every single person. But when it comes to handling medications and ADLs securely and gracefully, they frequently have peaceful benefits that households do not see on a brochure.
What "small" really suggests in assisted living
When I state small, I am speaking about neighborhoods that house roughly 6 to 40 citizens, not 80 to 200. In many states these are called residential care homes, board and care homes, or group homes. Some are regular houses that have been converted and licensed for elderly care; others are purpose‑built however still intimate.
Daily life in these settings feels different the minute you walk in. You hear personnel use given names without glancing at charts. You may see the very same caretaker who assisted with breakfast also assisting with medication tips and the afternoon shower. The building may not have a cinema or a beauty spa, however you can typically discover the nurse or administrator within a couple of steps.
That scale affects everything about medication management and ADL support.
The core obstacle: accuracy and pattern recognition
Managing medications and ADLs is not just a checklist exercise. It is a pattern recognition problem.
For medications, the threats are subtle. A missed out on blood pressure tablet may appear like a little additional fatigue. An unexpected double dose of insulin can become a medical emergency situation. The genuine ability lies in spotting small changes in appetite, mood, gait, or sleep that mean a medication concern before it escalates.
The very same holds true for ADLs. A person who suddenly struggles to button a shirt or gets confused in the shower may be dealing with discomfort, infection, dehydration, adverse effects of a brand-new drug, or cognitive decrease that has advanced. If nobody notifications for a week, one bad night can lead to a fall, a hospitalization, and an irreversible loss of independence.
Small assisted living neighborhoods have two structural advantages here: staff attention per resident and continuity of relationships.
More eyes on fewer residents
In a typical small community, frontline caregivers are responsible for a modest group, typically 4 to 8 locals per shift, in some cases less in higher‑acuity homes. In numerous bigger assisted living settings, those ratios can climb up much greater, especially on nights and nights.
That distinction changes how care is delivered.
In smaller settings, caretakers are simply closer to the rhythm of each resident's day. If Mrs. Alvarez generally consumes her entire omelet and all of a sudden leaves half untouched, the employee who serves breakfast is most likely the exact same one who manages her morning medication pass. They observe the change and can immediately ask: Did a pill feel stuck? Any queasiness? Did you sleep poorly? That real‑time loop is tough to reproduce in a larger building where departments are separated and staff rotate through broader zones.
This nearness appears strongly around ADLs. When a caregiver helps someone gown, they feel tightness in the shoulders that was not there last week. When they assist with bathing, they may see a brand-new bruise, a skin tear, or swelling around the ankles. Since the team is small and familiar, the caregiver is not handing off that observation to 3 other individuals; they are often informing the nurse or med tech straight, within minutes.
Over time, small discrepancies get dealt with early, rather than waiting on a quarterly care plan meeting while issues build up silently.
Medication management in a small community: what is different
Most states hold small and big assisted living communities to the exact same basic medication standards. Both should track medications, follow doctor orders, and file administration. The genuine difference comes in how those guidelines get lived out hour by hour.
Tighter medication routines and less handoffs
In small homes, the exact same individual or small group typically manages the medication pass for all citizens on a shift. There are less handoffs between med techs, and far fewer chances for "I believed you gave it" confusion.
Medication carts are simpler. You do not see 3 long corridors and 40 med drawers. You see a locked cabinet or a modest cart that holds medications for a handful of individuals who are frequently sitting right in front of you at the dining-room table.
Because of the scale, numerous small communities can schedule medication times around the resident, not simply the staffing grid. If Mr. Greene gets nauseated when he takes his early morning meds on an empty stomach, the group can easily shift his medications to line up with his breakfast routine, rather than forcing him into a stiff building‑wide passing schedule.
Better positioning between medications and daily life
It is something to read that a medication must be taken with food. It is another to stand at the counter and view whether a resident in fact swallows it while eating.
I have actually seen caregivers in small homes instinctively weave medication look into the flow of the day. They will set a cup of water by a resident's favorite recliner chair 15 minutes before the afternoon dose is due, then sit and chat while they confirm the tablets are taken. If there is a "PRN" medication purchased as required for pain or stress and anxiety, they frequently understand exactly how frequently it is genuinely required due to the fact that they have a feel for that resident's baseline mood and pain level.
That much deeper standard knowledge is critical for older adults who see multiple physicians. Numerous homeowners show up with complex programs: a medical care medical professional, a cardiologist, a neurologist, sometimes a pain expert. Each may change a couple of prescriptions, and without close observation, side effects blur into each senior care services BeeHive Homes of Taylor Ranch other. In a small setting, it is far more most likely that the very same caregiver notifications that the brand-new sleep medication has coincided with more daytime falls or that the dose increase has made somebody withdrawn.
When those patterns appear, a nurse or administrator can call the prescriber with concrete, day‑by‑day observations rather than unclear worries. That normally causes more exact modifications and fewer unnecessary drugs.
Fewer missed out on dosages and errors
No setting is immune to errors, but small communities normally have 3 useful safeguards:
- Staff who know homeowners by sight and personality, so it is more difficult to misidentify someone or forget their preferences.
- Slower, more focused med passes, since there are less people to serve in a short window.
- Less turnover in the med‑administration role, so routines become second nature.
I remember a resident in a 10‑bed home who had an aesthetically comparable bottle of vitamin D and a heart medication. Throughout a weekly internal audit, the supervisor noticed the capacity for confusion and separated the bottles, upgraded labeling, and re-trained the personnel. In a building with 100 citizens and dozens of medications per cart, capturing a small threat like that is much harder.
Families often stress that a smaller operation indicates less structure. In well‑run homes, the reverse is true: implementation of the guidelines is tighter since the team is small enough to hold each other accountable.
ADL assistance: where small homes silently shine
ADLs consist of bathing, dressing, grooming, toileting, transferring, and eating. When individuals tour communities, they often ask, "Do you help with showers?" or "Will somebody assistance Mom to the restroom at night?" That is only half the story. How the assistance is provided matters simply as much.
Care that moves at the resident's pace
In a bigger building, shower slots can feel like airport boarding groups: everybody slotted into a tight schedule so the staff can survive the list. That can work on paper but typically causes hurried, impersonal take care of homeowners who move gradually, are nervous in the restroom, or have actually dementia.
In smaller settings, there is more genuine versatility. If Mrs. Lin will only shower after her morning tea and Chinese news program, staff can generally respect that. If Mr. Rozier needs a quick sit‑down in between placing on pants and socks due to the fact that of cardiac arrest, the caretaker can allow for it without hindering a 30‑person schedule.
This pacing makes a substantial difference in dignity. People feel less like jobs to be completed and more like grownups being supported.
Fewer complete strangers, more trust
ADLs are intimate. Showering and toileting include vulnerability even when somebody is totally healthy. When cognitive decline enters the photo, unfamiliar faces can turn regular help into a struggle.

Small assisted living homes normally have a core team that citizens see daily. The very same caretaker who assists with breakfast often assists with toileting, transfers, and night routines. This consistency matters particularly in dementia care and respite care, where someone may just be staying a few weeks and has little time to adjust.
I have actually seen residents who were labeled "resistant to care" in larger centers become cooperative in a small home once a constant assistant learned the best approach. Often it was as easy as singing a preferred hymn during a shower or placing the towel on the resident's lap for modesty. One caretaker in a six‑bed home knew that Mr. Cline would only permit shaving if his grand son's photo was set on the bathroom counter initially. Those individualized tricks nearly never appear in a policy handbook, they emerge from duplicated, calm contact.
Early detection of decline
ADLs are the canary in the coal mine for health changes. A resident who can suddenly no longer stand from a toilet without aid might be developing brand-new weakness, experiencing a medication result, or starting a brand-new phase of cognitive decline.
In small neighborhoods, personnel generally notice within a day or 2 when someone's capabilities shift. They might point out, "She is needing more cues for shampooing," or "He is keeping the rails more and wincing when he steps into the tub." That type of concrete observation enables the nurse to reassess, involve physical therapy, or demand a medical assessment before a fall or injury occurs.
In a busier, bigger setting, incremental decreases can mix into the background sound of lots of citizens needing assistance simultaneously. Issues typically get flagged only after an occurrence, not before.
The household side: communication and partnership
Families who have actually been through a crisis know that medication and ADL management do not stop at the center door. Adult kids typically hold medical power of attorney, track specialist appointments, and act as historians for intricate health issue. In senior care, everything works much better when staff and family move in the very same direction.
Smaller assisted living homes are typically quicker to interact informal, low‑level modifications: a small cravings dip, new sleep patterns, small confusion, or a resident starting to require pointers to use the walker. Since there are fewer homeowners, personnel can fairly call or text families when something appears "off," instead of awaiting regular care strategy meetings.
I have actually sat at kitchen tables in care homes where a daughter and the administrator spread out tablet bottles, printed medication lists, and a hand‑drawn weekly schedule to figure out duplications after a hospitalization. That type of partnership is possible due to the fact that you are dealing with 10 or 20 locals, not 150.
For households utilizing respite care, where a loved one remains in assisted living for a short duration to provide the main caregiver a break, these communication practices are crucial. A two‑week stay can expose a lot: whether Mom really can manage her own medications in your home, whether Dad's nighttime roaming is more serious than it looked, whether a break from caretaker stress improves the resident's state of mind. Small neighborhoods generally have the time and intimacy to report back in beneficial detail, not simply "Whatever was fine."
Trade offs and when a bigger community might still be better
It would be misinforming to suggest that small assisted living neighborhoods are always remarkable. There are trade‑offs worth weighing.
Larger neighborhoods might offer onsite therapy fitness centers, more robust transport schedules, more recreational shows, and in some cases stronger 24‑hour medical staffing, especially in settings associated with health systems. For an extremely clinically complex resident who requires frequent on‑site nursing interventions, or for someone who grows on a busy social calendar with many activity choices, a larger structure can be a much better fit.
Small homes can vary extensively in quality. A 10‑bed house with strong management, stable staff, and clear processes can outshine an expensive school. A similar‑looking house with poor oversight can quickly become hazardous. Due to the fact that small settings are more personal, character clashes can feel enhanced. If a resident does not fit together with a tiny peer group, there is less opportunity to discover their "people" than in a bigger community.
Smaller homes might likewise have limitations on what they can safely handle. Some can not take locals who require mechanical lifts for transfers, who roam thoroughly, or who have unmanaged psychiatric conditions. They might likewise have less redundancy if a crucial team member is out sick.
The key is matching the resident's requirements and preferences with the strengths of the setting, then confirming that promised practices really occur.
Questions families ought to ask about medications and ADLs
When you tour a small assisted living community, it can help to bring concentrated concerns. A brief, targeted checklist keeps the discussion anchored in what really impacts safety and quality of life.
Here is one set of concerns worth asking about medication management:
- Who actually offers or supervises medications daily, and how are they trained?
- How lots of homeowners does that person deal with per shift?
- How do you manage brand-new prescriptions, terminated medications, or medical facility discharge orders?
- What is your process if a dosage is missed out on, refused, or vomited?
- How typically do you evaluate each resident's complete medication list with a nurse or pharmacist?
And for ADL support:
- How lots of citizens is each caretaker accountable for on day, night, and night shifts?
- Are the very same people usually aiding with bathing, dressing, and toileting, or does it alter frequently?
- How do you adjust routines for residents with dementia or stress and anxiety about bathing?
- What is your process when someone starts to require more assistance than before with an ADL?
- How quickly can you call household if you see a worrying modification in function?
Listening to how personnel response matters as much as the material. Clear, concrete explanations are an excellent indication. Unclear reassurances without specifics are not.
Signs that a small community is handling meds and ADLs well
You can typically identify strong medication and ADL practices through observation throughout a visit.
Residents appear tidy, appropriately dressed for the weather condition, and groomed in a way that fits their character. Clothes is not constantly mismatched or stained. You might see caregivers silently using cues instead of taking control of jobs that homeowners can still start by themselves, like placing a shirt in somebody's hands rather than dressing them completely.

Look at how staff talk to locals. Do they utilize calm, respectful tones? Do they explain what they are doing before assisting with personal care? When you view medication time, is it orderly and unhurried, with staff monitoring identity and keeping in mind any hesitations?
Pay attention to little information. A caretaker who notifications that Mrs. Patel constantly takes tablets more quickly with warm tea rather of cold water is most likely paying comparable attention to dozens of other preferences that make care much safer and kinder.
If you have permission, ask the administrator to stroll through a recent medication modification example, from physician's order to real implementation. Their capability to describe each action, including double‑checks and paperwork, tells you whether the system lives only on paper or in everyday practice.
Using respite care to "evaluate drive" a small community
Respite care can be an excellent method to evaluate how a small assisted living home handles medications and ADLs without dedicating to a long-term move. A stay of one to four weeks provides personnel time to learn your loved one's patterns and offers you a window into how they operate.
During respite, notification whether the neighborhood demands up‑to‑date medication lists, clarifies confusing prescriptions, and reports back any modifications they see. Ask how your family member tolerated showers, transfers, and toileting. Did staff determine any security issues in the house that you had actually missed out on, such as frequent nighttime restroom trips or unsteadiness when standing?
Families frequently come away from respite with one of two realizations. Either they feel validated that their loved one can safely stay at home with some additional assistance, or they see plainly that the structure and caution of a small community provide a level of elderly care that is tough to match at home.
Both results work. The point is not to hurry a permanent move, but to ground decisions in actual experience, not guesswork.
Bringing everything together
Medication and ADL management are where abstract guarantees of "quality senior care" meet the reality of tablets, baths, and bathroom journeys at 2 a.m. The quieter, less flashy strengths of small assisted living communities show up precisely there, in the details of how staff know and react to each resident's everyday rhythm.
Smaller settings tend to offer closer observation, more connection of caretakers, and more versatility to customize regimens around the individual rather than the building. That combination frequently causes earlier detection of health changes, fewer medication missteps, and a gentler, more respectful technique to intimate individual care.
That does not suggest every small home is exceptional or that bigger communities can not provide exceptional care. It means families assessing elderly care options ought to look beyond the size of the dining-room and ask comprehensive questions about who is watching, who is observing, and how quickly the team acts when something changes.
When you discover a small assisted living neighborhood where the responses are concrete, the personnel steady, and the homeowners unwinded and well attended, you are frequently taking a look at a location where medications are not just dispensed and ADLs are not simply completed, but where both are woven into a daily life that feels safe, human, and dignified.
BeeHive Homes of Taylor Ranch provides assisted living care
BeeHive Homes of Taylor Ranch provides memory care services
BeeHive Homes of Taylor Ranch provides respite care services
BeeHive Homes of Taylor Ranch supports assistance with bathing and grooming
BeeHive Homes of Taylor Ranch offers private bedrooms with private bathrooms
BeeHive Homes of Taylor Ranch provides medication monitoring and documentation
BeeHive Homes of Taylor Ranch serves dietitian-approved meals
BeeHive Homes of Taylor Ranch provides housekeeping services
BeeHive Homes of Taylor Ranch provides laundry services
BeeHive Homes of Taylor Ranch offers community dining and social engagement activities
BeeHive Homes of Taylor Ranch features life enrichment activities
BeeHive Homes of Taylor Ranch supports personal care assistance during meals and daily routines
BeeHive Homes of Taylor Ranch promotes frequent physical and mental exercise opportunities
BeeHive Homes of Taylor Ranch provides a home-like residential environment
BeeHive Homes of Taylor Ranch creates customized care plans as residents’ needs change
BeeHive Homes of Taylor Ranch assesses individual resident care needs
BeeHive Homes of Taylor Ranch accepts private pay and long-term care insurance
BeeHive Homes of Taylor Ranch assists qualified veterans with Aid and Attendance benefits
BeeHive Homes of Taylor Ranch encourages meaningful resident-to-staff relationships
BeeHive Homes of Taylor Ranch delivers compassionate, attentive senior care focused on dignity and comfort
BeeHive Homes of Taylor Ranch has a phone number of (505) 302-1919
BeeHive Homes of Taylor Ranch has an address of 6004 Whiteman Dr NW, Albuquerque, NM 87120
BeeHive Homes of Taylor Ranch has a website https://beehivehomes.com/locations/taylor-ranch/
BeeHive Homes of Taylor Ranch has Google Maps listing https://maps.app.goo.gl/VjePfgdypFLUTXAZ6
BeeHive Homes of Taylor Ranch has Instagram page https://www.instagram.com/beehivealbuquerquewest
BeeHive Homes of Taylor Ranch has an TikTok page https://www.tiktok.com/@beehivehomesalbuq
BeeHive Homes of Taylor Ranch has an YouTube page https://www.youtube.com/@hamiltonshives4468
BeeHive Homes of Taylor Ranch won Top Assisted Living Homes 2025
BeeHive Homes of Taylor Ranch earned Best Customer Service Award 2024
BeeHive Homes of Taylor Ranch placed 1st for Senior Living Communities 2025
People Also Ask about BeeHive Homes of Taylor Ranch
What is BeeHive Homes of Taylor Ranch Living monthly room rate?
Our base rate is $6,900 per month. We do an assessment of each resident's needs prior to move-in, so each resident's rate may be slightly higher. However, there are no "a la carte" charges or hidden fees. We do charge a one-time community move-in fee of $2,000
Does Medicare or Medicaid pay for a stay at Bee Hive Homes?
Medicare pays for hospital and nursing home stays, but does not pay for assisted living as a covered benefit. Some assisted living facilities are Medicaid providers, but we are not. We accept private pay, long-term care insurance, and we can assist qualified Veterans with approval for the Aid and Attendance program
Do we have a nurse on staff?
We do have a nurse on contract who is available as a resource to our staff but our residents' needs do not require a nurse on-site. We always have trained caregivers in the home and awake around the clock
What can you tell me about the food at Bee Hive?
You have to smell it and taste it to believe it! We use dietitian-approved menus with alternates for flexibility, and we can accommodate needs for different textures and therapeutic diets. We have found that most physicians are happy to relax diet restrictions without any negative effect on our residents
Do we allow pets?
We do allow small pets as long as the resident is able to care for them. State regulations also require that we have evidence of current immunizations for any required shots
Where is BeeHive Homes of Taylor Ranch located?
BeeHive Homes of Taylor Ranch is conveniently located at 6004 Whiteman Dr NW, Albuquerque, NM 87120. You can easily find directions on Google Maps or call at (505) 302-1919 Monday thru Sunday: 10:00am to 7:00pm
How can I contact BeeHive Homes of Taylor Ranch?
You can contact BeeHive Homes of Taylor Ranch by phone at: (505) 302-1919, visit their website at https://beehivehomes.com/locations/taylor-ranch/ or connect on social media via Instagram Facebook or TikTok
Residents may take a trip to the Boca Negra Canyon. Boca Negra Canyon offers a scenic Albuquerque destination where families visiting loved ones receiving Assisted living memory care senior care elderly care and respite care can enjoy an outdoor excursion.