Senior Care 101: How Assisted Living, Independent Living, and Nursing Homes Really Compare
Business Name: BeeHive Homes of Taylor Ranch
Address: 6004 Whiteman Dr NW, Albuquerque, NM 87120
Phone: (505) 302-1919
BeeHive Homes of Taylor Ranch
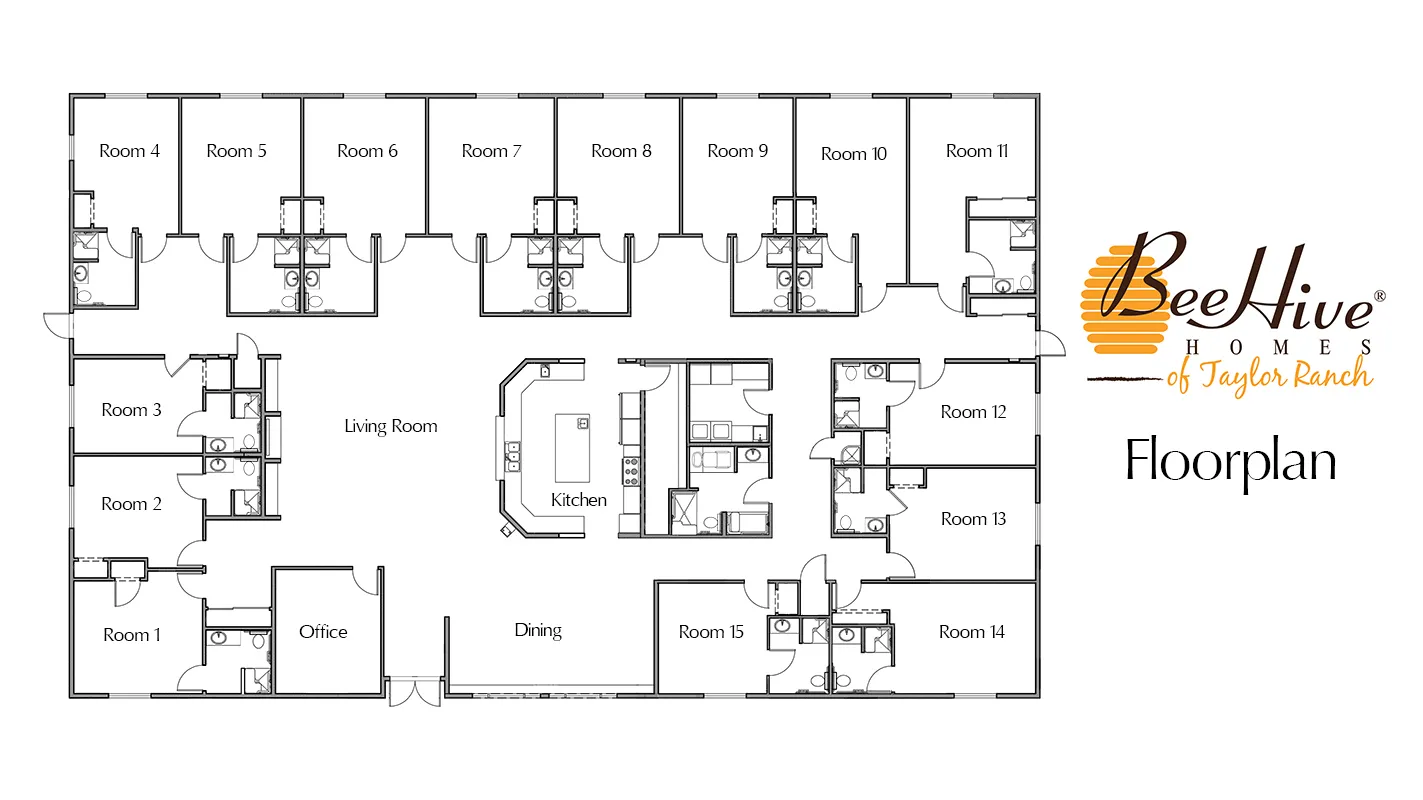
At BeeHive Homes of Taylor Ranch, New Mexico, we offer the finest assisted living experience available in a cozy, comfortable homelike setting. Each of our residents has their own spacious room with an ADA approved bathroom and shower. We prepare and serve delicious home-cooked meals three times a day every day. We maintain a small, friendly elderly care community. We provide regular activities that our residents find fun and contribute to their health and well-being. Our staff is attentive and caring and provides assistance with daily activities to our senior living residents in a loving and respectful manner. We would like to invite you to tour and experience our assisted living home and feel the difference.
6004 Whiteman Dr NW, Albuquerque, NM 87120
Business Hours
Families seldom begin looking into senior care because they have spare time and curiosity. The majority of get here in crisis or near it. A fall, a medical facility stay, a roaming occurrence, or an unexpected realization that the expenses are not being paid. Then the vocabulary starts flying: independent living, assisted living, skilled nursing, memory care, respite care. Everything noises technical, yet the decisions are deeply personal.
I have actually sat at plenty of kitchen tables with adult kids attempting to understand those words. They bring spreadsheets, regret, old promises about "never putting mom in a home," and a strong desire not to slip up. The reality is, there is no perfect setting. There are trade‑offs, and they look various for a fiercely independent 78‑year‑old than they do for a frail 92‑year‑old with advanced dementia.
What follows is a practical guide to how independent living, assisted living, and nursing homes operate in real life, how respite care fits in, and what tends to work best for different levels of need. The goal is not to offer you on a particular alternative, however to assist you see what these locations are actually like when the sales brochures are put away.
What these terms really mean
The senior care industry utilizes shorthand that confuses households. It assists to strip it back to the basics.
Independent living is housing with facilities customized for older grownups who are mainly self‑sufficient. Think about it as a house or cottage in a neighborhood where almost everybody is retired, meals and activities are available, and somebody will look at you if you are missing at supper, but you manage your own individual care and medical needs.
Assisted living is for older grownups who can no longer safely handle all day-to-day tasks alone, however do not require 24‑hour medical supervision. Personnel help with bathing, dressing, medications, and in some cases mobility. There is typically a nurse on site, but the setting feels residential, not clinical.
Nursing homes, likewise called skilled nursing centers, provide the greatest level of medical care outside a hospital. Citizens frequently have complicated medical conditions, need substantial assistance with daily activities, or require rehab after surgical treatment or disease. The environment is more managed, with certified nursing offered around the clock.
Respite care is short‑term care in any of these settings, normally for a couple of days to a few weeks. It is developed to give family caretakers a break, test‑drive a neighborhood, or cover gaps during illness, travel, or home modifications.
Within those broad classifications, quality and culture differ widely. 2 assisted living neighborhoods three miles apart can feel like completely various worlds. Regional policies likewise form what each type of community is permitted to do, specifically around medical tasks.
Key distinctions at a glance
A narrative description helps, however often you need a quick picture to orient you. The following comparison uses the normal design in lots of parts of the United States. Local rules, private communities, and other countries can differ, so treat this as a working map, not a legal definition.
-
Independent living: Residents are self‑sufficient, with optional assistance from outside services. Concentrate on way of life, socializing, and benefit rather than medical care.
-
Assisted living: Homeowners need routine help with individual care or medications however do not need consistent nursing oversight. Personnel assistance every day life, and the setting aims to seem like home.
-
Nursing home: Homeowners have severe, ongoing medical or functional requirements. Accredited nurses are present at all times, and healthcare, rehab, and guidance are central.
-
Respite care: Short‑term stay, generally in assisted living or a nursing home. Supplies momentary elderly care when household support is not readily available or needs relief.
This structure helps you match your relative's requirements with the best level of senior care before you get lost in sales tours.
Independent living: Liberty with a security net
Independent living is frequently the initial step out of a long‑time home. It works best for older adults who are still managing their own medications, finances, and individual care however are tired of home maintenance or are feeling too isolated.
From the resident's perspective, the appeal is uncomplicated. No more snow shoveling, roofing leaks, or stressing who will fix the hot water heater. Meals can be provided, though many citizens still like to prepare. There are neighbors in similar life stages, and activities varying from book clubs to fitness classes. Transportation to medical consultations is common.
The tricky part is that independent living is not a medical design. Staff are not anticipated to aid with bathing, toileting, or hands‑on transfer help. They are not typically tracking blood sugars or high blood pressure. If a resident begins to fall regularly, forgets to eat, or mishandles medications, the community will typically recommend employing in‑home caregivers or moving to assisted living.
Families in some cases misjudge this. I have seen independent living houses filled with grab bars, walkers, and pill organizers, plus a resident who is clearly overwhelmed. On paper, they "live independently." In practice, their quality of life is bad, and they are one broken hip far from a forced move.
Independent living works well when:
- The older adult values privacy and control, and still deals with day-to-day tasks reliably.
- There is some regional support, whether from family or paid services, that can step in as needs change.
- The individual is socially open enough to take advantage of neighborhood life, or a minimum of neutral toward it.
It can be a bad fit if isolation, medication confusion, or risky mobility are currently significant problems. Transferring to independent living in that circumstance typically purchases just a short window before another move is needed.
Assisted living: Assistance for everyday life
Assisted living beings in the middle of the senior care spectrum, and for numerous older grownups it is the sweet spot. The resident has their own apartment or condo or suite. They bring their furniture, pictures, and favorite chair. Meals, housekeeping, and laundry are dealt with. Staff assist with individual care, and someone is constantly close by.
At its finest, assisted living protects dignity while silently wrapping a net around the vulnerable parts of day-to-day routine. A resident might need help actioning in and out of the shower however can clean their own hair. Or they can dress themselves if someone sets out the clothes. Or they are psychologically sharp however physically limited by Parkinson's or serious arthritis.
Medication management is typically the single most important service. In lots of assisted living communities, staff shop and administer medications, track refills, and coordinate with drug stores. For people handling blood pressure tablets, blood thinners, diabetes medications, and more, this is not a high-end. It prevents ER visits.
However, households sometimes expect assisted living to function like a small healthcare facility. That is not reasonable. Assisted living personnel are trained in elderly care and personal assistance, however they are not staffed like an intense care unit.
Typical limits in assisted living consist of:
- Residents generally need to be medically stable. Major oxygen needs, unmanaged behaviors, or quickly changing conditions might require a higher level of care.
- Most communities can not offer constant one‑on‑one guidance, such as for a resident who tries to stand and walk every couple of minutes despite severe fall risk.
- There are normally guidelines around lifting and transfers. If a resident needs 2 staff members to transfer securely, not every assisted living website can accommodate that.
From an expense point of view, assisted living is often personal pay. Regular monthly fees differ widely by area however can vary from the low thousands to well over six thousand dollars per month, depending on apartment or condo size and care level. Care charges are frequently tiered: as needs increase, so do costs.
Families need to look beyond the design. Observe how personnel talk to citizens in the hallways and dining room. Ask how they handle falls, how frequently care plans are evaluated, and what occurs if the resident's needs increase. Communities that answer these questions plainly and without deflecting provide a much better safety net over time.
Nursing homes: Healthcare and long‑term support
Nursing homes occupy a challenging place in public creativity. Many older grownups say, sometimes strongly, "I never ever want to end up in a home." That fear is rooted in older designs of institutional care and in really real stories of poor‑quality centers. It is also real that for some people, a good experienced nursing facility is the most safe, most suitable option.
Nursing homes offer 24‑hour nursing supervision, medication administration, wound care, feeding assistance, and rehabilitation treatments such as physical, occupational, and speech therapy. Residents may be short‑term, recuperating from joint replacement, stroke, or major infection. Or they may be long‑term, living there for several years with advanced dementia, extreme mobility limitations, or intricate medical needs.
The environment is more medical. You will see med carts, lifts, therapy health clubs, and personnel in scrubs. Laws are more stringent than in assisted living. There are care plan meetings, regular physician oversight, and comprehensive documentation requirements.
From a useful perspective, somebody may need a nursing home if:
- They are bedbound or require total help for mobility and individual care.
- They have regular or complicated medical interventions: feeding tubes, IV medications, advanced wound care, or complex respiratory support.
- Their cognitive or behavioral signs need structured guidance that assisted living can not securely provide.
One subtlety many households learn the difficult way: short‑term rehabilitation stays are frequently covered for a minimal time by insurance coverage or national health systems after a certifying healthcare facility stay, however long‑term custodial care (assist with bathing, dressing, toileting) is usually not covered the exact same way. People run out of rehab days or coverage and shift to personal pay or public long‑term care programs. Comprehending this monetary shift early prevents panicked choices later.
Quality distinctions across nursing homes are plain. In some, call lights ring constantly, homeowners sit plunged in wheelchairs, and personnel turnover is consistent. In others, staff understand residents by nickname, treatment is proactive, and households feel included. Exploring at various times of day, talking with households in the lobby, and asking staff how long they have worked there typically tells you more than any rating website.

Where respite care fits in
Respite care is among the most underused tools in senior care. It is momentary residential care that gives family caregivers a break or bridges a shift. Respite can take place in assisted living, a nursing home, or often specialized short‑stay units.
Typical circumstances:
A daughter looking after her father with mid‑stage dementia requires to take a trip for work for a week. She arranges a 10‑day respite remain in a memory‑capable assisted living neighborhood. Her father gets structured activities and supervision; she gets to do her job without constant worry.
A partner caregiver is tired however feels guilty admitting it. A social worker suggests a two‑week respite in a skilled nursing center. During that time, the partner has their own medical consultations, captures up on sleep, and evaluates whether home care remains realistic.
An older adult is released from the medical facility after pneumonia. They are still weak, and the family is unsure if they can manage in the house securely. A short rehabilitation stay in a nursing home functions as respite and as a trial run. If strength returns, they can return home or to independent living. If not, the household has more time to prepare long‑term arrangements.
Respite care slots can be restricted, especially throughout peak times like vacations. They almost always require advance preparation, upgraded medical information, and an evaluation to validate the setting can meet the person's needs. For many families, however, respite is the pressure valve that prevents burnout or unsafe caregiving situations.
Daily life: What really changes from one setting to another
Brochures tend to highlight facilities. Homeowners and households care more about how the day unfolds.
In independent living, early mornings depend nearly totally on the resident's choices. Some sleep late and consume coffee in their kitchenette. Others head straight to the dining-room. Personnel might sign in subtly, for instance by noting who has not come to meals, but there is no expectation that citizens follow a particular schedule.
In assisted living, everyday rhythms are formed by care needs. Personnel develop schedules for bathing support, medication rounds, and housekeeping. A resident may receive help with showering twice weekly, medication administration three times daily, and help getting ready in the early morning and at bedtime. Activities are provided at set times, yet citizens still have freedom to pick whether to join.
In nursing homes, the structure is tighter. Medication administration, treatments, and treatment sessions follow scientific routines. Meals occur on schedule, often with assigned seating in dining-room or provided at the bedside. Versatility is possible, particularly in higher‑quality facilities, however daily life is more regulated simply because scientific tasks should be completed.
Families in some cases worry that structure equates to loss of autonomy. In truth, for somebody living with substantial impairment, structure can feel supporting. The key is whether personnel technique routines with regard and cooperation. "How would you like to begin your morning?" feels extremely different from "Time to get up, we need to get this done."
Safety, self-respect, and risk: Discovering a workable balance
One of the hardest parts of senior care preparation is stabilizing security with autonomy. Specialists in elderly care discuss "dignity of risk" - the concept that adults have the right to make choices that involve some danger, as long as they comprehend and accept the consequences.
In practice, this looks various in each setting:
In independent living, the community may highly encourage fall prevention procedures, however citizens can still decrease grab bars or choose to utilize a rolling office chair rather of a stable dining chair. As long as they have the ability to make educated decisions, their right to deal with risk is broad.
In assisted living, the lines are blurrier. Staff are accountable for resident security, yet they are likewise expected to honor choices. If a resident with a history of falls insists on walking without a walker, the care team will likely involve the family, record the conversation, and try to work out. They may schedule physical treatment to assess gait or schedule supervised walks.
In nursing homes, security concerns bring much more weight because regulative analysis and liability threats are high. That does not remove resident rights, but it narrows the variety of appropriate threats. For example, a resident who eliminates a fall alarm may still be allowed to do so, however personnel needs to show that they evaluated cognition, educated the resident, and implemented alternative measures.
Families often lean heavily toward safety, particularly after a scare. Older grownups tend to lean toward independence, particularly if they already feel their world shrinking. The healthiest choices generally come from sincere conversations where both point of views are called and respected, rather than hurried choices made in the shadow of a crisis.
Money: How expenses and coverage actually work
Money shapes senior care alternatives more than most households wish to admit. It is uneasy to put a dollar sign next to quality of life, however overlooking expenses does not make them disappear.
Independent living is generally personal pay. Monthly charges vary based upon place, size of system, and included services. Energies, meals, housekeeping, and social programming are often bundled. Medical insurance seldom covers this setting due to the fact that it is considered housing, not medical care.
Assisted living is likewise usually personal pay, with some regional exceptions for limited public funding programs. Base lease covers the house and fundamental services. Care charges are added based upon an evaluation of requirements, like support with bathing, dressing, or medication management. As needs grow, month-to-month costs often increase.
Nursing homes are more complicated. Short‑term competent rehab after a medical facility stay may be partly or completely covered for a specified duration, if particular requirements are met. Long‑term residence for custodial care is various. Protection depends greatly on country and regional policies, however lots of people either pay privately till they qualify for public long‑term care programs, or they depend on a mix of private funds and public subsidies from the start.
Respite care can be private pay or supported by caregiver support programs, long‑term care insurance, or local social services. Coverage rules vary widely. Many families presume respite is covered, only to find out that advantages are limited or require preauthorization.
A frank early conversation with a monetary coordinator, elder law lawyer, or social worker who understands local benefits saves heartbreak later on. Excellent preparation thinks about not just month-to-month charges, but likewise what occurs if the older adult lives longer than expected, ends up being widowed, or requires to relocate to a higher level of care.
How health modifications push the requirement to step up care
People hardly ever move directly from independent living to a nursing home without something changing. Patterns usually emerge.
For example, memory decrease begins as small lapses: lost secrets, a missed visit. Then expenses accumulate, appliances are left on, driving ends up being doubtful. Initially, in‑home help can compensate. Gradually, the threat of leaving the stove on or wandering in the evening may make assisted living with memory care a much better option.
Mobility issues follow another path. A person with arthritis may walk more gradually, but safely, for many years. Add a stroke or a hip fracture, and suddenly transfers, toileting, and bathing require 2 individuals and special equipment. At that point, assisted living may no longer be able to meet transfer requirements, and a nursing home ends up being the more secure choice.
Chronic illness can tip the balance too. Somebody with heart failure and diabetes might handle well in independent or assisted living for a long period of time with excellent outpatient care. Several hospitalizations in a year, getting worse shortness of breath, or duplicated medication changes may signal that closer clinical oversight is required.
Families typically feel guilty when health modifications force a move. They view it as a failure to honor guarantees or to "keep mom at home." A more precise frame is that the individual's needs developed, and the care environment required to progress with them. That is not a broken pledge. It is responsible adaptation.
Questions to ask when you tour a community
When you walk into a senior community, it is easy to be swayed by chandeliers or, on the other side, by a faint disinfectant odor. Particular concerns grounded in how care works will inform you far more.
-
What takes place if my member of the family's requirements increase? Can they stay here, or would they need to move?
-
How do you manage falls, medical emergencies, and hospital transfers throughout nights and weekends?
-
Who offers medications, how are changes communicated, and how do you lower errors?
-
How do you recognize and respond to isolation, isolation, or depression among residents?
-
Can you describe a current challenging situation with a resident and how your team dealt with it?
Ask personnel for concrete examples and listen carefully to how they discuss citizens. Do they utilize considerate language? Do they understand homeowners' stories? Do they explain families as partners or as obstacles?
After the tour, trust your quieter impressions too. How did homeowners look and sound? Did staff appear rushed or present? Did anybody talk straight to the older adult you are supporting, or did they only resolve you?
Matching the individual to the place
Choosing among independent living, assisted living, nursing homes, and respite care is less about labels and more about fit.
A 79‑year‑old retired instructor who still drives, volunteers, and manages her own medications might thrive in independent living, acquiring buddies and dropping the problems of home ownership. A 90‑year‑old widower with moderate dementia, unstable walking, and weight-loss might regain stability in assisted living, with constant meals, social contact, and cueing for hygiene and medications. A 75‑year‑old stroke survivor who is immobilized on one side and has a feeding tube will likely be most safe in a nursing home with round‑the‑clock nursing and rehabilitation.
Senior care decisions work best when they begin early, before a devastating occasion. Even one exploratory tour of a community before it elder care BeeHive Homes of Taylor Ranch is urgently required changes the tone later. The older grownup has a possibility to state, "I liked that location with the garden," or "I will never live someplace that smells like bleach," and those choices can assist the family when crisis comes.
No setting can remove the vulnerabilities that age and illness bring. The real objective is more modest and more significant: select a location that supports as much self-reliance as is safely possible, protects from avoidable damage, and permits the older adult to stay an individual with a history and a voice, not simply a list of medical diagnoses and tasks.
Independent living, assisted living, nursing homes, and respite care are tools. Used attentively, each can supply comfort, safety, and self-respect at various points along the aging journey. The obstacle is not to select the best tool at last, but to keep adjusting the fit as life unfolds.
BeeHive Homes of Taylor Ranch provides assisted living care
BeeHive Homes of Taylor Ranch provides memory care services
BeeHive Homes of Taylor Ranch provides respite care services
BeeHive Homes of Taylor Ranch supports assistance with bathing and grooming
BeeHive Homes of Taylor Ranch offers private bedrooms with private bathrooms
BeeHive Homes of Taylor Ranch provides medication monitoring and documentation
BeeHive Homes of Taylor Ranch serves dietitian-approved meals
BeeHive Homes of Taylor Ranch provides housekeeping services
BeeHive Homes of Taylor Ranch provides laundry services
BeeHive Homes of Taylor Ranch offers community dining and social engagement activities
BeeHive Homes of Taylor Ranch features life enrichment activities
BeeHive Homes of Taylor Ranch supports personal care assistance during meals and daily routines
BeeHive Homes of Taylor Ranch promotes frequent physical and mental exercise opportunities
BeeHive Homes of Taylor Ranch provides a home-like residential environment
BeeHive Homes of Taylor Ranch creates customized care plans as residents’ needs change
BeeHive Homes of Taylor Ranch assesses individual resident care needs
BeeHive Homes of Taylor Ranch accepts private pay and long-term care insurance
BeeHive Homes of Taylor Ranch assists qualified veterans with Aid and Attendance benefits
BeeHive Homes of Taylor Ranch encourages meaningful resident-to-staff relationships
BeeHive Homes of Taylor Ranch delivers compassionate, attentive senior care focused on dignity and comfort
BeeHive Homes of Taylor Ranch has a phone number of (505) 302-1919
BeeHive Homes of Taylor Ranch has an address of 6004 Whiteman Dr NW, Albuquerque, NM 87120
BeeHive Homes of Taylor Ranch has a website https://beehivehomes.com/locations/taylor-ranch/
BeeHive Homes of Taylor Ranch has Google Maps listing https://maps.app.goo.gl/VjePfgdypFLUTXAZ6
BeeHive Homes of Taylor Ranch has Instagram page https://www.instagram.com/beehivealbuquerquewest
BeeHive Homes of Taylor Ranch has an TikTok page https://www.tiktok.com/@beehivehomesalbuq
BeeHive Homes of Taylor Ranch has an YouTube page https://www.youtube.com/@hamiltonshives4468
BeeHive Homes of Taylor Ranch won Top Assisted Living Homes 2025
BeeHive Homes of Taylor Ranch earned Best Customer Service Award 2024
BeeHive Homes of Taylor Ranch placed 1st for Senior Living Communities 2025
People Also Ask about BeeHive Homes of Taylor Ranch
What is BeeHive Homes of Taylor Ranch Living monthly room rate?
Our base rate is $6,900 per month. We do an assessment of each resident's needs prior to move-in, so each resident's rate may be slightly higher. However, there are no "a la carte" charges or hidden fees. We do charge a one-time community move-in fee of $2,000
Does Medicare or Medicaid pay for a stay at Bee Hive Homes?
Medicare pays for hospital and nursing home stays, but does not pay for assisted living as a covered benefit. Some assisted living facilities are Medicaid providers, but we are not. We accept private pay, long-term care insurance, and we can assist qualified Veterans with approval for the Aid and Attendance program
Do we have a nurse on staff?
We do have a nurse on contract who is available as a resource to our staff but our residents' needs do not require a nurse on-site. We always have trained caregivers in the home and awake around the clock
What can you tell me about the food at Bee Hive?
You have to smell it and taste it to believe it! We use dietitian-approved menus with alternates for flexibility, and we can accommodate needs for different textures and therapeutic diets. We have found that most physicians are happy to relax diet restrictions without any negative effect on our residents
Do we allow pets?
We do allow small pets as long as the resident is able to care for them. State regulations also require that we have evidence of current immunizations for any required shots
Where is BeeHive Homes of Taylor Ranch located?
BeeHive Homes of Taylor Ranch is conveniently located at 6004 Whiteman Dr NW, Albuquerque, NM 87120. You can easily find directions on Google Maps or call at (505) 302-1919 Monday thru Sunday: 10:00am to 7:00pm
How can I contact BeeHive Homes of Taylor Ranch?
You can contact BeeHive Homes of Taylor Ranch by phone at: (505) 302-1919, visit their website at https://beehivehomes.com/locations/taylor-ranch/ or connect on social media via Instagram Facebook or TikTok
You might take a short drive to the New Mexico Museum of Natural History and Science. The New Mexico Museum of Natural History and Science offers educational exhibits and multigenerational experiences for families connected with Assisted living memory care senior care elderly care and respite care.